
GLP-1 Myths: What the Evidence Actually Says
GLP-1 medications are surrounded by claims about diabetes, injections, muscle loss, compounded drugs, weight regain, thyroid cancer, and mental health. Here’s what current evidence actually supports.

Table of Contents
- Myth 1: "GLP-1 Medications Are Only for Diabetes"
- What the evidence says: False.
- Myth 2: "All GLP-1 Medications Are Injections"
- What the evidence says: No longer true.
- Myth 3: "GLP-1 Drugs Are Basically Insulin"
- What the evidence says: False.
- Myth 4: "GLP-1 Medications Melt Fat"
- What the evidence says: That's an oversimplification.
- Myth 5: "All the Weight You Lose Is Muscle"
- What the evidence says: False — but lean-mass loss deserves attention.
- Myth 6: "Everyone Loses the Same Amount of Weight"
- What the evidence says: False.
- Myth 7: "Compounded Semaglutide or Tirzepatide Is Exactly the Same as the FDA-Approved Product"
- What the evidence says: False.
- Myth 8: "Once You Reach Your Goal Weight, You Can Stop the Medication and the Weight Will Automatically Stay Off"
- What the evidence says: Research shows substantial weight regain can occur after treatment is stopped.
- What the evidence says: FDA's current conclusion is the opposite.
- Myth 10: "The Thyroid Cancer Warning Means GLP-1 Drugs Have Been Proven to Cause Thyroid Cancer in Humans"
- What the evidence says: That is not what the warning says.
- Bonus Myth: "Lifestyle Doesn't Matter Once You're Taking a GLP-1"
- What the evidence says: FDA-approved weight-management indications still include lifestyle measures.
- Myth vs Evidence at a Glance
- Why GLP-1 Misinformation Spreads So Easily
- The science changes quickly
- Brand names create confusion
- Clinical-trial averages become social-media guarantees
- Risk gets stripped of context
- Five Questions to Ask When You Hear a GLP-1 Claim
- Where Should You Get Medication Information?
- Provider Choice Still Matters
- The Bottom Line
Few medication categories have generated as much conversation — and misinformation — as GLP-1-related medications.
Claims appear on social media every day:
"They're only diabetes drugs."
"GLP-1s make you lose all your muscle."
"The compounded version is exactly the same."
"Everyone gains all the weight back."
"They cause thyroid cancer."
Some claims contain a piece of truth but leave out important context.
Others are simply outdated.
Here are 10 common GLP-1 myths and what current evidence actually supports.
Medication information reviewed September 2026.
Educational information only. GoLean Horizon does not provide medical advice, prescribe medication, recommend a medication, or determine treatment eligibility. A licensed healthcare provider determines whether treatment is medically appropriate.
Myth 1: "GLP-1 Medications Are Only for Diabetes"
What the evidence says: False.
GLP-1 receptor agonists were originally developed and widely used for type 2 diabetes.
But several FDA-approved products now have indications beyond diabetes.
For example:
- Wegovy (semaglutide) is FDA approved for chronic weight management in certain people with obesity or overweight.
- Zepbound (tirzepatide) is approved for chronic weight management in certain adults.
- Foundayo (orforglipron) was approved in April 2026 for long-term weight reduction in certain adults.
- Wegovy also has certain cardiovascular and other approved indications.
A person does not necessarily need diabetes to have an FDA-approved indication for one of these medications.
The specific product and indication matter.
Myth 2: "All GLP-1 Medications Are Injections"
What the evidence says: No longer true.
Injectable GLP-1 medications remain common.
But oral options now exist.
Current FDA-approved oral weight-management options include:
- Wegovy tablets — semaglutide
- Foundayo — orforglipron
These are taken by mouth.
Their administration instructions are not identical.
For example, oral Wegovy has specific fasting and water requirements, while Foundayo does not require administration on an empty stomach.
For a detailed comparison, read:
Oral vs Injectable GLP-1 Options: What Should You Know?
Myth 3: "GLP-1 Drugs Are Basically Insulin"
What the evidence says: False.
GLP-1 receptor agonists are not insulin.
GLP-1 is a hormone involved in:
- appetite regulation
- food intake
- glucose-dependent insulin secretion
- glucagon regulation
- gastric emptying
Some medications activate only the GLP-1 receptor.
For example:
semaglutide → GLP-1 receptor
Tirzepatide works differently:
tirzepatide → GIP + GLP-1 receptors
These pathways can influence glucose metabolism, but the drugs themselves are not insulin.
For more:
Semaglutide vs Tirzepatide: What's the Difference?
Myth 4: "GLP-1 Medications Melt Fat"
What the evidence says: That's an oversimplification.
GLP-1-related medications do not directly "melt" fat.
They can influence:
- appetite
- hunger
- fullness
- food intake
- gastric emptying
- glucose regulation
When calorie intake decreases and body weight falls, the body can lose both:
fat mass
and
lean mass
The changes are biological consequences of weight reduction, not a drug selectively dissolving body fat.
Myth 5: "All the Weight You Lose Is Muscle"
What the evidence says: False — but lean-mass loss deserves attention.
Weight loss generally includes some lean tissue loss, whether weight reduction occurs through lifestyle intervention, medication, surgery, or other methods.
A body-composition substudy of the SURMOUNT-1 tirzepatide trial found that approximately:
75% of weight lost was fat mass
and
25% was lean mass
in the studied participants.
That does not mean every person will experience exactly that ratio.
And "lean mass" is not identical to skeletal muscle.
A 2026 systematic review cautioned that lean mass is not synonymous with skeletal-muscle loss or sarcopenia, and that current evidence on muscle preservation during GLP-1 treatment remains limited and heterogeneous.
Recent research also cautions against assuming that lean-mass measurements tell us everything about muscle strength, muscle quality, or physical function.
So both extremes are misleading:
"GLP-1s cause no lean-mass loss"
and
"GLP-1s make you lose all your muscle."
The better discussion involves nutrition, adequate protein when appropriate, resistance exercise, overall activity, age, health status, and individual monitoring.
Myth 6: "Everyone Loses the Same Amount of Weight"
What the evidence says: False.
Clinical trials report averages across groups.
They do not predict exactly what will happen to one individual.
People can respond differently because of factors such as:
- medication
- dose
- treatment duration
- side effects
- ability to continue treatment
- health conditions
- other medications
- eating patterns
- physical activity
- individual biology
If a clinical trial reports an average weight reduction of a certain percentage, some participants lost more.
Some lost less.
Some discontinued treatment.
An average is not a guarantee.
This is also why comparing medications only by a single headline percentage can be misleading.
Myth 7: "Compounded Semaglutide or Tirzepatide Is Exactly the Same as the FDA-Approved Product"
What the evidence says: False.
FDA-approved and compounded drugs are not the same regulatory category.
FDA-approved medications undergo FDA review for:
- safety
- effectiveness
- manufacturing quality
Compounded medications do not undergo FDA premarket review for safety, effectiveness, or quality.
FDA has also warned about dosing errors, adverse events, illegally marketed GLP-1 products, and certain compounded products using semaglutide salt forms that differ from the active ingredient used in FDA-approved semaglutide products.
As of May 31, 2026, FDA reported receiving hundreds of adverse-event reports associated with compounded semaglutide and compounded tirzepatide, while noting that causality cannot always be determined and that reporting for many compounders is not mandatory.
This does not mean compounding never has an appropriate role.
It means:
compounded does not mean FDA approved
and
compounded does not mean identical.
Ask:
- What exact medication am I receiving?
- Is it FDA approved?
- If compounded, why is compounding being used?
- Which pharmacy is preparing it?
- Is that pharmacy appropriately licensed?
Myth 8: "Once You Reach Your Goal Weight, You Can Stop the Medication and the Weight Will Automatically Stay Off"
What the evidence says: Research shows substantial weight regain can occur after treatment is stopped.
This does not mean every person regains every pound.
But randomized withdrawal studies show that regain can be substantial.
In an extension of the STEP 1 semaglutide trial, participants who stopped semaglutide regained about two-thirds of their previous weight loss over the following year, on average.
Research involving tirzepatide has shown a similar general pattern.
In SURMOUNT-4, people who stopped tirzepatide experienced substantial weight regain, while those who continued treatment maintained and added to their earlier weight reduction.
Explore My Options
Compare provider options based on factors such as cost, flexibility, support, medication preferences, and overall experience.
Explore My OptionsGoLean Horizon provides educational information and provider-matching resources. A licensed healthcare provider determines whether treatment is medically appropriate.
A 2026 analysis also found that most participants who had tirzepatide withdrawn regained at least 25% of the weight they had previously lost within a year.
These findings do not mean every patient must take the same medication forever.
They do show that obesity can require ongoing management.
Decisions about continuing, changing, tapering, or stopping treatment should be individualized with a healthcare professional.
---## Myth 9: "FDA Found That GLP-1 Drugs Cause Suicidal Thoughts"
What the evidence says: FDA's current conclusion is the opposite.
FDA investigated reports of suicidal thoughts and behavior associated with GLP-1 receptor agonists.
After reviewing available evidence, FDA announced in January 2026 that it did not identify an increased risk of suicidal ideation or behavior associated with GLP-1 receptor agonist medications.
FDA therefore requested removal of the suicidal-behavior and ideation warning from labeling where it had appeared for:
- Saxenda
- Wegovy
- Zepbound
This is a good example of why older social-media posts or articles can become outdated.
Safety surveillance continues even after medications reach the market.
Anyone experiencing suicidal thoughts or major mood changes should still seek appropriate medical help regardless of what medication they are taking.
Myth 10: "The Thyroid Cancer Warning Means GLP-1 Drugs Have Been Proven to Cause Thyroid Cancer in Humans"
What the evidence says: That is not what the warning says.
Several GLP-1-related products carry an FDA boxed warning about:
thyroid C-cell tumors
For semaglutide and tirzepatide, thyroid C-cell tumors occurred in rodents.
FDA labeling states that it is unknown whether these medications cause thyroid C-cell tumors, including medullary thyroid carcinoma, in humans because the relevance of the animal findings to humans has not been determined.
That does not mean the warning should be ignored.
Products such as Wegovy and Zepbound are contraindicated in people with:
- a personal history of medullary thyroid carcinoma
- a family history of medullary thyroid carcinoma
- Multiple Endocrine Neoplasia syndrome type 2, or MEN 2
So both statements below go too far:
"GLP-1 medications definitely cause thyroid cancer in people."
and
"The thyroid warning doesn't matter."
The accurate statement lies between them:
There is an important FDA warning based substantially on animal findings, while a causal thyroid-cancer risk in humans has not been established.
Bonus Myth: "Lifestyle Doesn't Matter Once You're Taking a GLP-1"
What the evidence says: FDA-approved weight-management indications still include lifestyle measures.
FDA approvals for medications such as Wegovy, Zepbound, and Foundayo specify their use together with measures such as:
- reduced-calorie diet
- increased physical activity
Medication can influence hunger, appetite, food intake, and metabolism.
But it does not make:
- nutrition
- physical activity
- strength
- hydration
- sleep
- follow-up care
irrelevant.
Those factors are also important for overall health beyond what happens on the scale.
Myth vs Evidence at a Glance
| Myth | What Current Evidence Supports |
|---|---|
| GLP-1 drugs are only for diabetes | Several products have FDA-approved weight-management indications |
| All GLP-1s are injections | FDA-approved oral options now exist |
| GLP-1 drugs are insulin | They act through incretin-related pathways; they are not insulin |
| They melt fat | They influence appetite, food intake and metabolic pathways |
| All weight loss is muscle | Both fat and lean mass can decrease; fat accounted for most loss in a tirzepatide substudy |
| Everyone loses the same amount | Trial averages hide substantial individual variation |
| Compounded means identical | Compounded medications are not FDA approved and are a different regulatory category |
| Weight automatically stays off after stopping | Withdrawal trials show substantial regain can occur |
| FDA says they cause suicidal thoughts | FDA's 2026 review did not find an increased risk |
| Thyroid cancer in humans is proven | Animal findings prompted boxed warnings; human causation remains uncertain |
Why GLP-1 Misinformation Spreads So Easily
There are several reasons.
The science changes quickly
New:
- medications
- formulations
- doses
- indications
- safety reviews
continue to appear.
Information accurate two years ago may already be incomplete.
Brand names create confusion
For example:
Wegovy and Ozempic both contain semaglutide
but they are not simply interchangeable labels for the same FDA indication.
Likewise:
Zepbound and Mounjaro both contain tirzepatide
but their approved indications differ.
Clinical-trial averages become social-media guarantees
A group average gets transformed into:
"You will lose X%."
That is not how clinical-trial data should be interpreted.
Risk gets stripped of context
A boxed warning may become:
"This drug causes cancer."
An adverse-event report may become:
"FDA proved the medication caused it."
Neither interpretation necessarily follows from the evidence.
Five Questions to Ask When You Hear a GLP-1 Claim
Before believing or sharing a claim, ask:
- Is the claim about a specific medication or the entire category?
- Is it based on an FDA label, clinical trial, observational study, case report, or social-media anecdote?
- Was the medication FDA approved or compounded?
- Does the evidence show association or actual causation?
- How recent is the information?
This matters particularly in a field changing as quickly as GLP-1 treatment.
Where Should You Get Medication Information?
Useful sources include:
- FDA prescribing information
- FDA drug-safety communications
- licensed healthcare professionals
- pharmacists
- peer-reviewed clinical research
Be more cautious with claims based primarily on:
- testimonials
- influencer videos
- screenshots without sources
- advertisements
- anonymous posts
- dramatic before-and-after examples
Personal experiences can be meaningful.
But one person's experience cannot establish what a medication will do for everyone else.
Provider Choice Still Matters
Medication information is only part of the picture.
When comparing GLP-1 telehealth providers, ask:
- Who reviews my health information?
- Which medication options are offered?
- Is the medication FDA approved or compounded?
- Which pharmacy is used?
- How does follow-up work?
- What does the price include?
- Can I contact a clinician with questions?
Read:
7 Questions to Ask Before Choosing a GLP-1 Provider
To understand what to expect after you sign up with a telehealth provider:
What Happens After Signup? A GLP-1 Telehealth Walkthrough
The Bottom Line
GLP-1 medications are real prescription therapies with:
documented benefits
known risks
remaining uncertainties
and
rapidly evolving evidence.
The most accurate view is rarely found at either extreme.
They are not:
miracle drugs with no risks
and they are not:
automatically dangerous medications with no legitimate medical role.
Current evidence supports a more useful approach:
Know the exact medication.
Understand the FDA-approved indication.
Distinguish approved from compounded products.
Understand benefits and risks.
Treat clinical-trial averages as averages — not promises.
Use current evidence rather than viral claims.
And let an appropriately licensed healthcare professional determine whether treatment is medically appropriate for you.
Sources & References
- 1.FDA — GLP-1 Suicidal Behavior and Ideation Safety Communication, January 2026: FDA's review did not identify an increased risk and it requested removal of the warning from affected labels.
- 2.FDA — Concerns With Unapproved GLP-1 Drugs Used for Weight Loss: primary source for compounded medications, semaglutide salts, dosing concerns, adverse-event reports, and the FDA-approved versus compounded distinction.
- 3.FDA — Zepbound Approval for Chronic Weight Management: supports approved weight-management indications, GIP/GLP-1 mechanism, and use with reduced-calorie diet and physical activity.
- 4.FDA — Foundayo Approval, April 2026: supports the current availability of an FDA-approved oral GLP-1 weight-management medication.
- 5.Wilding et al. — STEP 1 Trial Extension: primary evidence for weight regain following withdrawal of semaglutide 2.4 mg.
- 6.SURMOUNT-4 Randomized Clinical Trial: primary evidence for maintenance versus regain after continuation or withdrawal of tirzepatide.
- 7.SURMOUNT-1 Body Composition Substudy: supports the nuanced fat-mass and lean-mass discussion.
- 8.FDA — Wegovy Prescribing Information: supports the boxed warning and FDA statement that human relevance of rodent thyroid C-cell tumors has not been established.
- 9.FDA — Zepbound Prescribing Information: supports the equivalent thyroid-warning discussion for tirzepatide.
Frequently Asked Questions
Are GLP-1 medications only for people with diabetes?
No. Several FDA-approved products have indications for chronic weight management in people meeting specified criteria, including people who do not have diabetes. Zepbound, for example, was approved for chronic weight management in certain adults with obesity or overweight.
Do GLP-1 medications cause muscle loss?
Weight loss can include both fat and lean mass. In a tirzepatide body-composition substudy, approximately 75% of lost weight was fat mass and 25% lean mass. Lean mass is not synonymous with skeletal muscle, and current research does not support the claim that all GLP-1-associated weight loss is muscle.
Will I regain weight if I stop a GLP-1 medication?
Substantial regain occurred on average in randomized withdrawal research involving semaglutide and tirzepatide, but individual outcomes vary. Medication continuation or discontinuation should be discussed with the prescribing healthcare professional.
Are compounded GLP-1 medications identical to FDA-approved products?
No. Compounded medications are not FDA approved and do not undergo FDA's premarket review for safety, effectiveness, and manufacturing quality.
Did FDA find that GLP-1 medications cause suicidal thoughts?
No. In January 2026, FDA said its comprehensive review did not identify an increased risk of suicidal ideation or behavior with GLP-1 receptor agonists and requested removal of that warning from affected product labeling.
Do GLP-1 medications cause thyroid cancer in humans?
Some products carry boxed warnings because thyroid C-cell tumors occurred in animal studies. FDA labeling states that it is unknown whether semaglutide or tirzepatide causes these tumors in humans. The medications remain contraindicated in people with certain MTC or MEN 2 histories.
Are all GLP-1 medications injections?
No. FDA-approved oral options now exist, including Foundayo (orforglipron), which FDA approved in April 2026 for certain adults with obesity or overweight.
Explore My Options
Compare provider options based on factors such as cost, flexibility, support, medication preferences, and overall experience.
Explore My OptionsGoLean Horizon provides educational information and provider-matching resources. A licensed healthcare provider determines whether treatment is medically appropriate.
Educational information only. GoLean Horizon does not provide medical advice, prescribe medication, or determine treatment eligibility. A licensed healthcare provider determines whether treatment is medically appropriate.
Continue Learning


Oral vs Injectable GLP-1 Options: What Should You Know?
GLP-1-related medications now include both oral and injectable options. Learn how pills and injections differ in dosing frequency, administration, approved uses, convenience, safety, and other practical considerations.


What Happens After You Sign Up for a GLP-1 Telehealth Program?
After signing up for a GLP-1 telehealth program, you may complete a health intake, undergo licensed provider review, answer follow-up questions, receive next-step instructions, and learn how prescriptions, pharmacy fulfillment, follow-up, and refills work.

7 Questions to Ask Before Choosing a GLP-1 Provider
Before choosing a GLP-1 telehealth provider, ask what the price includes, who reviews your information, whether medication and follow-up are included, how refills work, and what requirements apply.

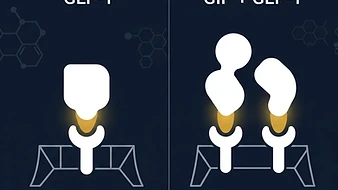
Semaglutide vs Tirzepatide: What's the Difference?
Semaglutide and tirzepatide are both used in FDA-approved medications for weight management and type 2 diabetes, but they work differently. Learn about GLP-1 vs GIP/GLP-1 activity, indications, weight-loss evidence, side effects, dosing, and other differences.